
Peripartum cardiomyopathy
Conditions
Overview
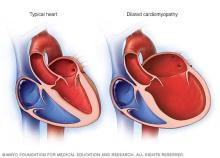
Peripartum cardiomyopathy (kahr-dee-o-my-OP-uh-thee) is a disease of the heart muscle that happens during pregnancy or soon after delivery. Peripartum means the time around childbirth.
Usually, peripartum cardiomyopathy (PPCM) happens during late pregnancy or in the months right after the baby is born. Another name for the condition is pregnancy-associated cardiomyopathy. When it starts after delivery, it also may be called postpartum cardiomyopathy.
PPCM is not common. The exact number of people who develop it is not known. But it can be serious. In people with PPCM, the heart's main pumping chamber, called the left ventricle, gets weak. The heart can't squeeze hard enough to pump blood to the rest of the body. This can lead to heart failure.
It's thought that hormone changes that happen during pregnancy may play a role in peripartum cardiomyopathy. Some people have a gene change that makes them more likely to get the condition.
Treatment of peripartum cardiomyopathy depends on your symptoms and how well the heart pumps blood. If you are still pregnant, your care team also thinks about the health of your baby. Peripartum cardiomyopathy can get better with treatment. Medicines can help the heart pump better and ease symptoms. In many people with PPCM, the heart gets stronger over time. For others, the heart gets stronger but does not fully recover. But in some people, the heart stays very weak. In those people, a heart transplant may be needed.
Types
There are different types of cardiomyopathy. This article focuses on peripartum cardiomyopathy (PPCM).
PPCM is similar to dilated cardiomyopathy. But PPCM is considered a separate condition that happens during pregnancy or in the months after delivery.
Another type is hypertrophic cardiomyopathy. Some people may already have this type of cardiomyopathy before pregnancy or learn they have it during pregnancy.
Symptoms
Peripartum cardiomyopathy (PPCM) usually occurs during late pregnancy or the months after delivery. Some symptoms can seem like changes that naturally happen during pregnancy or after delivery. For example, you may feel very tired.
PPCM symptoms happen when the heart can't pump blood as it should. The condition causes symptoms of heart failure. Symptoms can include:
- Shortness of breath or trouble breathing with activity or even at rest.
- Trouble breathing when you lie flat.
- A cough while lying down.
- Feeling very tired, even after getting rest.
- Swelling in your legs, ankles or feet.
- Fast or pounding heartbeats.
- Fainting or feeling dizzy or lightheaded.
- Chest discomfort or pain, mostly after physical activity or heavy meals.
In some people, the symptoms get worse quickly.
When to seek care
Call your healthcare professional if you are pregnant or recently gave birth and have any of these symptoms:
- Shortness of breath that is new or getting worse.
- Chest discomfort.
- Fast or pounding heartbeats.
- Swelling that is new or getting worse.
When to seek emergency care
Peripartum cardiomyopathy (PPCM) can cause heart failure.
Call 911 or your local emergency number if you have symptoms such as:
- Severe weakness.
- Sudden, severe shortness of breath or very fast breathing.
- Chest pain that is not explained or lasts for more than a few minutes.
- Very fast or pounding heartbeats with shortness of breath, chest pain or fainting.
- Weak pulse.
- Low blood pressure.
- Urinating less than usual or not at all.
These symptoms may happen when the heart can't pump blood as it should. But there are many other possible causes. At the emergency room, healthcare professionals do tests to learn if your symptoms are due to heart failure or something else.
Causes
The exact cause of peripartum cardiomyopathy is not known. Researchers think several changes may work together to weaken the heart. These changes may include:
- Hormone changes. The body may break down a hormone called prolactin into a form that harms heart muscle and blood vessels. Prolactin is the hormone involved in making breast milk.
- Changes in blood vessels during pregnancy. The placenta grows during pregnancy to give the baby oxygen and nutrients. It also makes substances that may harm blood vessels. This may weaken the heart.
- Genetics. Some people with PPCM have changes in genes that are linked with another heart condition that weakens the heart muscle. That condition is called dilated cardiomyopathy. Researchers are still learning how genes and pregnancy work together to cause PPCM.
Risk factors
Some things make you more likely to get peripartum cardiomyopathy. But having a risk factor does not mean that you will definitely develop PPCM. Some risk factors cannot be changed.
Risk factors for peripartum cardiomyopathy may include:
- Preeclampsia, a pregnancy complication that involves high blood pressure, high levels of protein in the urine and signs of organ damage.
- High blood pressure during pregnancy.
- Pregnancy with twins or other multiples.
- Being age 30 or older during pregnancy.
- Some gene changes, especially changes in a gene called TTN.
- Not having enough healthy red blood cells, called anemia.
- Race. PPCM is much more likely to develop in Black women than it is in white women.
Complications
Peripartum cardiomyopathy can lead to serious health conditions, including:
- Heart failure. The heart can't pump enough blood to meet the body's needs. Without treatment, heart failure can be life-threatening. Some people may need a heart device to help the heart pump.
- Blood clots. Because the heart can't pump well, blood clots might form in the heart. If clots enter the bloodstream, they can block the blood flow to other organs, including the heart and brain.
- Cardiogenic shock. This is a life-threatening condition that happens when the heart can't pump enough blood to the body's organs.
- Heartbeats that are not regular. Peripartum cardiomyopathy can cause the heart to become larger. This can cause changes in the heartbeat, called arrhythmias.
- Sudden cardiac arrest and sudden cardiac death. Cardiomyopathy can trigger heartbeat changes that cause the heart to stop beating. This can lead to sudden cardiac death.
Prevention
If you are pregnant, go to all your pregnancy care visits. Tell your healthcare professional about any new symptoms or if any symptoms get worse. If you have had PPCM before, talk with your cardiologist and pregnancy care team before another pregnancy. PPCM can come back during a future pregnancy.
Diagnosis
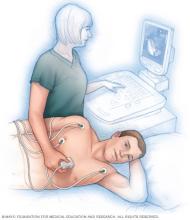
To diagnose peripartum cardiomyopathy (PPCM), your healthcare professional examines you. You usually are asked questions about your symptoms and health history.
Before diagnosing PPCM, your healthcare team does tests to rule out other conditions that could cause your symptoms. One condition is myocarditis, which is swelling and irritation of the heart muscle. Myocarditis can weaken the heart. It can look like PPCM.
Peripartum cardiomyopathy is diagnosed when:
- Heart failure starts near the end of pregnancy or in the months after delivery.
- Tests such as an echocardiogram show that the heart is not pumping as strongly as it should.
- No other cause of the heart failure is found.
Blood tests
A blood test can't tell for sure whether you have peripartum cardiomyopathy. But blood tests can help your healthcare team look for signs of heart failure.
Blood tests to look for heart failure in people with PPCM may include:
- B-type natriuretic peptide (BNP) and NT-proBNP. Levels of these substances in the blood can go up when the heart is under stress, such as during heart failure.
- Troponin. This is a protein found in heart muscle. Higher levels of the protein may mean there is heart damage.
You may have other blood tests, depending on your symptoms.
Echocardiogram
An echocardiogram is the main test for peripartum cardiomyopathy (PPCM). The test uses sound waves to make moving pictures of the heart. Another name for this test is an ultrasound of the heart.
An echocardiogram shows how blood flows through the heart and heart valves. A measurement taken during the test shows how much blood your lower left chamber pushes out with each heartbeat. This measurement is called the ejection fraction. The result is given as a percentage. Peripartum cardiomyopathy usually causes an ejection fraction below 45%.
Other tests
Other tests can help your healthcare team look for changes in your heart and heartbeat. These tests may be used to rule out other conditions that can cause similar symptoms.
- Electrocardiogram (ECG). This quick and painless test shows how the heart is beating. Sticky patches with sensors on them, called electrodes, go on the chest and sometimes the arms and legs. Wires connect the electrodes to a computer, which prints or shows the test results. The test may show changes in heart rate or rhythm. An ECG cannot diagnose PPCM by itself.
- Chest X-ray. A chest X-ray shows the condition of the lungs and heart. It can show whether the heart is larger than usual or if there is fluid buildup in the lungs. These things can happen with heart failure.
- Cardiac MRI. This test uses magnetic fields and radio waves to make images of the heart. It can give your healthcare team more information about the heart's structure and how well it pumps. This test may be done if the images from an echocardiogram aren't enough to tell for sure if you have cardiomyopathy. A cardiac MRI can help rule out other causes of heart failure.
Genetic testing
Sometimes cardiomyopathy is due to a gene change that can be passed down through families. Ask your healthcare professional if genetic testing is right for you.
Treatment
If you have peripartum cardiomyopathy (PPCM), a team of healthcare professionals work together to treat your condition and support your care. You do not have to manage the condition on your own. Your healthcare team depends on your specific needs but may include:
- A doctor trained in pregnancy and childbirth, called an obstetrician.
- A doctor trained in high-risk pregnancies, called a maternal-fetal medicine specialist.
- Doctors trained in heart conditions, called cardiologists.
- Heart failure specialists.
- A primary healthcare professional.
The goals of peripartum cardiomyopathy (PPCM) treatment are to:
- Manage symptoms.
- Keep the condition from getting worse.
- Lower the risk of complications.
The type of treatment depends on:
- The type of cardiomyopathy and how serious it is.
- How weak your heart is.
- Whether you are pregnant or just had your baby.
Medicines
Many types of medicines are used to treat peripartum cardiomyopathy (PPCM). Medicines can help:
- Improve blood flow and help the heart pump better.
- Lower blood pressure.
- Slow heart rate.
- Remove extra fluid and sodium from the body.
- Prevent blood clots.
Medicines for PPCM may include:
- Diuretics. These medicines help your body get rid of extra fluid.
- Beta blockers. These medicines slow the heartbeat. They can help the heart pump better.
- Medicine that widens blood vessels. These medicines make it easier for the heart to pump blood through the body. They include hydralazine and isosorbide dinitrate. The medicines may be given separately or combined in one pill.
- A blood thinner called heparin. This medicine helps prevent blood clots. You may need it if you are at a high risk of blood clots. A weak heart can raise the risk of blood clots.
- Bromocriptine. This medicine is used to treat Parkinson disease, type 2 diabetes, high prolactin levels and some other conditions. It may be used for some people with severe PPCM. But it is still being studied as a treatment for PPCM.
Some heart failure medicines can harm a developing baby. These include ACE inhibitors and angiotensin 2 receptor blockers, called ARBs. They are not used during pregnancy. Your care team carefully chooses medicines that fit your needs during pregnancy. The team also considers if you are breastfeeding. Some medicines that are not used during pregnancy, such as some ACE inhibitors, may be used while breastfeeding. Talk with your care team about your treatment and feeding plans.
Heart devices
Some people with peripartum cardiomyopathy (PPCM) may need a heart device. A very weak heart can cause dangerous heartbeat changes. A heart device may help control these changes or help the heart pump blood.
Heart devices include:
- Implantable cardioverter-defibrillator (ICD). This device is placed in the chest. It constantly watches the heartbeat. The device gives an electric shock if needed to stop a dangerous heartbeat. Some people may get a temporary defibrillator that can be worn outside the body instead while the healthcare team waits to see if the heart gets stronger. This is called a wearable cardioverter-defibrillator.
- Pacemaker. A pacemaker prevents the heart from beating too slowly. The device is placed under the skin near the collarbone.
- Cardiac resynchronization therapy (CRT). This is a treatment for some people who have heart failure. It helps the lower heart chambers squeeze at the same time. This helps the heart better pump blood to the body.
- Ventricular assist device (VAD). A VAD helps pump blood from the lower chambers of the heart to the rest of the body. It's a treatment for a weakened heart or heart failure. A VAD may be used to help the heart work while waiting for other treatments, such as a heart transplant.
Cardiac ablation
Some people with severe peripartum cardiomyopathy (PPCM) may have dangerous changes in their heartbeat. They may need a treatment called cardiac ablation. Ablation is not a treatment for PPCM itself.
During ablation, a doctor places one or more catheters into blood vessels to the heart. Sensors at the catheter tips use heat or cold energy to create tiny scars in the heart. The scars block signals that cause irregular heartbeats.
Heart transplant
A heart transplant is surgery to replace a damaged heart with a healthy heart from a person who is no longer living.
Most people with PPCM do not need a heart transplant. It may be an option if PPCM causes severe heart failure and the heart does not get better with other treatments. Some people may have a ventricular assist device (VAD) to help the heart pump while waiting for a transplant.
A transplant may improve quality of life. However, some people who have a heart transplant for PPCM may have a somewhat lower chance of survival after transplant than people who get a transplant for other heart conditions.
Talk to your pregnancy heart team and heart doctors about the risks and benefits of all PPCM treatments.
Labor and delivery
If you have peripartum cardiomyopathy (PPCM) while you are pregnant, your heart and pregnancy care teams work with you to plan your labor and delivery. Your treatment and care depend on how well your heart is pumping. They also depend on how you and your baby are doing.
If you and the baby are doing well, vaginal delivery is usually recommended. A C-section may be needed if your condition gets more serious or for other pregnancy reasons.
During labor and delivery, your healthcare team usually:
- Watches you closely. Your blood pressure, heartbeat, breathing and fluid levels are typically checked.
- Watches your baby's heartbeat. Your baby's heart rate may be watched continuously during anesthesia, labor and delivery. This is called continuous fetal heart rate monitoring.
- Gives you medicine for pain. You may get pain medicine through a small tube placed in your lower back. This is called an epidural. It can help keep labor pain from putting extra strain on your heart.
- Helps with pushing, if needed and if you're having a vaginal delivery. Sometimes, forceps or a vacuum device may be used to help deliver the baby. This can make the pushing part of labor shorter. It also can put less stress on your heart.
After delivery, you need regular checkups by a healthcare professional. Changes in blood flow and body fluids after birth can put extra strain on a weak heart.
Prognosis
The outlook for peripartum cardiomyopathy (PPCM) is different for each person. Many people get better over time. The heart often gets stronger during the first few months of treatment.
But for some people, it takes longer. The heart may stay weak. Black women are less likely than white women to have the heart get back to its earlier strength. The reasons are not fully known. Changes in genes or things in the environment may play a part. Black women also may be diagnosed later after giving birth. This delay may affect how well the heart recovers.
How well the heart pumps when PPCM is found can give your healthcare team clues about how much it may improve.
Future pregnancies
If you've had peripartum cardiomyopathy (PPCM), the condition can happen again during a future pregnancy. Your chance is higher if your heart is still weak before getting pregnant again. But PPCM can come back even if the heart has improved.
Talk with your cardiologist and pregnancy care team before planning another pregnancy. Tests can be done to see how well your heart is pumping. Together, you and your healthcare team can talk about what another pregnancy may mean for you.
Lifestyle and home remedies
You can take an active part in your care. Follow the peripartum cardiomyopathy (PPCM) treatment plan from your care team. Your care team may ask you to:
- Check your weight every day. Quick weight gain can be a sign that your body is holding extra fluid.
- Be as physically active as possible. The amount and type of activity depend on how well your heart is working and how you feel. Your healthcare team can tell you what types of activity are safe for you.
- Watch how much salt you eat. PPCM can cause heart failure. Heart failure can make fluid build up in the body. Too much salt can make the body hold even more fluid. This can make swelling and shortness of breath worse.
Preparing for an appointment
If you think you may have peripartum cardiomyopathy or are worried about your risk, see your healthcare professional. You might first see your pregnancy healthcare professional. You also may be sent to a heart doctor, called a cardiologist.
Here's information to help you get ready for your appointment.
What you can do
When you make the appointment, ask if there's anything you need to do in advance. For example, you may be told not to eat or drink for a short while before some blood tests.
Make a list of:
- Your symptoms. Include any that may not seem related to your heart. Note when your symptoms began.
- Important personal information. Include any family history of cardiomyopathy, heart disease, stroke, high blood pressure or diabetes. Also note any major stresses or recent life changes.
- All medicines, vitamins or other supplements you take. Include those you bought without a prescription. Include the doses.
- Questions to ask your healthcare team.
Take a family member or friend along if you can. This person can help you remember the information you're given.
For cardiomyopathy, some basic questions to ask your healthcare professional include:
- What's the most likely cause of my symptoms?
- What are other possible causes?
- What tests do I need?
- What treatment options are available, and which do you recommend for me?
- Can I breastfeed?
- What should I know about a future pregnancy?
- How often do I need heart tests?
- Should I or my family members have genetic testing?
- I have other health conditions. How can I best manage these conditions together?
- Is there any information that I can take home with me? What websites do you recommend?
What to expect from your doctor
Your healthcare team is likely to ask you questions such as:
- Do you have symptoms all the time, or do they come and go?
- On a scale of 1 to 10, with 10 being the worst, how bad are your symptoms?
- What, if anything, makes your symptoms better?
- What, if anything, makes your symptoms worse?
© 1998-2026 Mayo Foundation for Medical Education and Research(MFMER). All rights reserved. Terms of Use