
Triple-positive breast cancer
Conditions
Overview
Triple-positive breast cancer (TPBC) is a type of breast cancer. Like other types of breast cancer, TPBC starts as a growth of cells in the breast. What makes TPBC different from other types is that the cancer cells use the hormones estrogen and progesterone to help them grow. The cells also make extra HER2 protein.
This type of breast cancer is called triple positive because the cells test positive for three things: estrogen receptors, progesterone receptors and HER2 protein. Because of these results, TPBC has more treatment options than other breast cancer types. Treatment with estrogen blocker therapy medicines can stop hormones from helping the cancer grow. Targeted therapy medicines may help treat this cancer by attacking cells that make too much HER2 protein.
Which treatments your healthcare team recommends may depend on the cancer's stage and other factors. Treatments may include surgery, radiation therapy and medicines.
When it's found in the early stages, TPBC often can be cured. Even when a cure isn't possible, treatments can slow the growth of the cancer and help extend your life.
Research and information often include TPBC in the larger category of HR-positive, HER2-positive breast cancer.
Symptoms
Triple-positive breast cancer (TPBC) often doesn't cause symptoms at first. When symptoms happen, they often are similar to those of other breast cancers.
TPBC signs and symptoms may include:
- An area of thickening in part of the breast that makes it feel different from the surrounding tissue.
- A nipple that looks flattened or turns inward.
- A change in breast skin color. The skin may look pink, red, purple or brown, or darker than the surrounding skin.
- Change in the size, shape or appearance of a breast.
- Changes to the skin over the breast, such as skin that looks dimpled or looks like an orange peel.
- Peeling, scaling, crusting or flaking of the skin on the breast.
When to see a healthcare professional
Make an appointment with a healthcare professional if you notice a change in your breasts, such as a lump, skin that looks puckered, thickening under the skin or nipple discharge. Report these changes even if you recently had a mammogram.
Causes
The exact cause of triple-positive breast cancer (TPBC) often isn't known. Healthcare professionals know that it starts when changes happen in the DNA inside breast cells. But exactly what causes these genetic changes isn't always known.
DNA gives cells instructions for when to grow, divide and die. Changes in DNA can cause breast cells to grow out of control and live longer than they should. These extra cells can form a tumor.
Some DNA changes that lead to cancer are passed from parents to children. These are called inherited DNA changes.
Not everyone with an inherited DNA change gets cancer. Most people who get cancer don't have an inherited DNA change. It's likely that TPBC is caused by inherited and other factors.
The DNA changes that lead to triple-positive breast cancer (TPBC) can cause the cancer cells to grow into nearby tissue.
Over time, cancer cells can break away and spread to other parts of the body. When cancer spreads, it's called metastatic cancer. Like other breast cancers, triple-positive breast cancer most often spreads to the bones, lungs, liver and brain.
Risk factors
The risk factors for triple-positive breast cancer (TPBC) are similar to those for breast cancer in general. Factors that raise the risk of breast cancer in general include:
- A family history of breast cancer. If a parent, sibling or child had breast cancer, your risk of breast cancer is increased. The risk is higher if your family has a history of getting breast cancer at a young age. The risk also is higher if you have multiple family members with breast cancer. Still, most people diagnosed with breast cancer don't have a family history of the disease.
- A personal history of breast cancer. If you've had cancer in one breast, you have an increased risk of getting cancer in the other breast.
- A personal history of breast conditions. Certain breast conditions are markers for a higher risk of breast cancer. If you've had a breast biopsy that found one of these conditions, you have an increased risk of breast cancer.
- Sex at birth. Breast cancer is much more common in women. But anyone with breast tissue can get breast cancer.
- Younger age when periods start. Beginning your period before age 12 increases your risk of breast cancer.
- Older age when menopause starts. Beginning menopause after age 55 increases the risk of breast cancer.
- Dense breast tissue. Breast tissue is made up of fatty tissue and dense tissue. Fatty tissue is made of fat. Dense tissue is made of milk glands, milk ducts and fibrous tissue. If you have dense breasts, you have more dense tissue than fatty tissue in your breasts. Having dense breasts increases the risk of developing breast cancer and makes it harder to detect cancer on a mammogram. Talk with your healthcare team about other tests you might have in addition to mammograms to look for breast cancer.
Other risk factors include:
- Drinking alcohol. Drinking alcohol increases the risk of breast cancer.
- Having your first child at an older age. Giving birth to your first child after age 35 may increase the risk of breast cancer.
- Having never been pregnant. Having been pregnant one or more times lowers the risk of breast cancer. Never having been pregnant increases the risk.
- Inherited DNA changes that increase cancer risk. Certain DNA changes that increase the risk of breast cancer can be passed from parents to children. The most well-known changes are called BRCA1 and BRCA2. These changes can greatly increase your risk of breast cancer and other cancers, but not everyone with these DNA changes gets cancer.
- Menopausal hormone therapy. Taking certain hormone therapy medicines to manage the symptoms of menopause may increase the risk of breast cancer. The risk is linked to hormone therapy medicines that combine estrogen and progesterone.
- Older age. The risk of breast cancer increases as you age. Triple-positive breast cancer can happen at any adult age but tends to happen at an older age compared with other types of breast cancer.
- Obesity. People with obesity have an increased risk of breast cancer.
- Radiation exposure. Radiation treatments to the chest during childhood or young adulthood raise the risk of breast cancer.
Prevention
There is no sure way to prevent triple-positive breast cancer (TPBC). But you can take steps to help lower your risk of triple-positive breast cancer and other types of breast cancer.
Ask about breast cancer screening
Talk with a healthcare professional about when to begin breast cancer screening. Ask about the benefits and risks of screening. Together, you can decide what breast cancer screening tests are right for you.
Become familiar with your breasts
Perform occasional breast self-exams to become familiar with how your breasts usually look and feel. Tell a healthcare professional if you notice any new changes.
Drink alcohol in moderation, if at all
For breast cancer prevention, there is no safe amount of alcohol. If you choose to drink alcohol, limit how often you drink and keep the amount small. If you're concerned about your breast cancer risk, you may choose not to drink alcohol.
Exercise most days of the week
Aim for at least 30 minutes of exercise on most days of the week. If you haven't been active lately, ask a healthcare professional whether it's OK and start slowly.
Limit menopausal hormone therapy
Hormone therapy that uses a combination of estrogen and progesterone may increase the risk of breast cancer. Talk with a healthcare professional about the benefits and risks of hormone therapy.
Maintain a healthy weight
Ask a healthcare professional what weight range is healthy for you. If weight loss is recommended, ask about what changes to diet and exercise can be made to reach that goal.
Talk with a healthcare professional about your cancer risk
If you have a family history of breast cancer or think that you may have an increased risk of breast cancer, talk about it with your healthcare professional. Preventive medicines, surgery and more-frequent screening may be options for people with a high risk of breast cancer.
Diagnosis
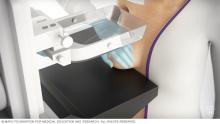
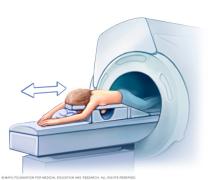
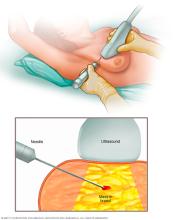
Diagnosing triple-positive breast cancer (TPBC) and other breast cancers often begins with a breast exam and a discussion of your symptoms. Imaging tests, such as a mammogram, ultrasound or MRI, can show areas that need a closer look. A tissue sample is needed to confirm whether cancer is present.
Breast exam
During a breast exam, a healthcare professional looks for changes in the breast skin or nipples and feels the breasts, collarbone areas and armpits for lumps.
Mammogram
A mammogram is an X-ray of the breast tissue. Mammograms are commonly used to screen for breast cancer. If a screening mammogram finds something concerning, you might have another mammogram to look at the area more closely. This more-detailed mammogram is called a diagnostic mammogram. It's often used to look closely at both breasts.
Breast ultrasound
Ultrasound uses sound waves to make pictures of structures inside the body. A breast ultrasound may give your healthcare team more information about a breast lump. For example, an ultrasound might show whether the lump is a solid mass or a fluid-filled cyst. The healthcare team uses this information to decide what tests you might need next.
Breast MRI
MRI machines use a magnetic field and radio waves to create pictures of the inside of the body. A breast MRI can make more-detailed pictures of the breast. Sometimes this method is used to look closely for any other areas of cancer in the affected breast.
It also might be used to look for cancer in the other breast. Before a breast MRI, you usually receive an injection of contrast. The contrast material helps the tissue show up better in the images. MRI helps show the size of triple-positive breast cancer when the cancer is hard to see on other imaging tests.
Breast biopsy
A biopsy is a procedure to remove a sample of tissue for testing in a lab. For a breast biopsy, a healthcare professional often puts a needle through the skin and into the breast tissue. The healthcare professional guides the needle using images created with X-rays, ultrasound or another type of imaging. Once the needle is in place, the healthcare professional uses it to remove tissue. Often, a marker is placed in the spot where the tissue sample was removed. This small metal marker will show up on imaging tests. The marker helps your healthcare team mark the area of concern.
Lab testing
The tissue sample from a biopsy goes to a lab for testing. Tests can show whether the cells in the sample are cancerous. Other tests give more details about the cells. A pathologist reviews the biopsy sample in a lab. A pathologist is a healthcare professional who looks for disease in cells, body fluids and tissue.
Results are often given in a pathology report. Your pathology report may include:
- Cell type. The results show whether the cancer cells are ductal cells, lobular cells or other kinds of cells.
- Cell grade. The grade of the breast cancer cells is based on how the cells look under a microscope. The grade tells the healthcare team whether the cancer is likely to grow slowly or quickly.
- Hormone receptor status. Breast cancer cells may use the hormones estrogen and progesterone to help them grow. Hormone receptors are proteins that estrogen or progesterone can attach to. If the cancer has receptors for one or both hormones, it is hormone receptor positive. If testing doesn't find receptors, then the cancer is hormone receptor negative. TPBC is hormone receptor positive for estrogen and progesterone.
- HER2 status. HER2 is a protein that helps cells grow. A cancer is HER2 positive if its cells have too much HER2 protein or extra copies of the HER2 gene. TPBC is HER2 positive.
- Ki-67 score. Ki-67 is a protein that marks how fast the cancer cells divide, also called the proliferation rate. The Ki-67 score goes from 0% to 100%. A higher score suggests a higher rate of dividing cells and faster growth.
The healthcare team uses the results from lab tests to decide on the cancer's stage, understand the prognosis and make a treatment plan.
Treatment
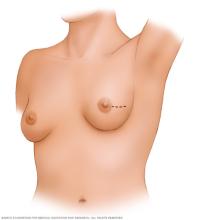
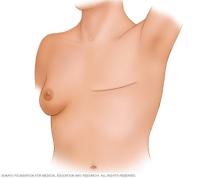
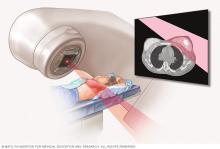
Treatment for triple-positive breast cancer (TPBC) may begin with surgery or medicines, depending on the cancer's stage and features.
Some things to note about TPBC include:
- Triple-positive breast cancers are sensitive to hormones. Breast cancers that are sensitive to hormones are called hormone receptor (HR) positive. These cancers may respond to treatments that block hormones in the body, called estrogen blocker therapy.
- Triple-positive breast cancers make extra HER2. TPBC cells have too much HER2 protein or extra copies of the HER2 gene. Medicines can target HER2 or its growth signals.
Your treatment plan will depend on many factors. Your healthcare team considers the stage of the cancer and how quickly it grows. Your care team also considers your overall health and what you prefer.
Breast cancer surgery
Breast cancer surgery typically involves a procedure to remove the breast cancer and, sometimes, a procedure to remove some nearby lymph nodes. Surgical procedures used to treat TPBC include:
- Lumpectomy. A lumpectomy is surgery to remove the breast cancer and some of the healthy tissue around it. It allows you to maintain most of your breast. Other names for this surgery are breast-conserving surgery and wide local excision. Most people have radiation therapy after lumpectomy.
- Mastectomy. A mastectomy is surgery to remove all breast tissue from a breast. Total mastectomy, also called simple mastectomy, removes all of the breast, including the lobules, ducts, fatty tissue and some skin, including the nipple and areola. Other procedures include skin-sparing mastectomy, which leaves the skin, and nipple-sparing mastectomy, which leaves the areola, nipple and skin.
- Lymph node surgery. Lymph node surgery removes nearby lymph nodes to check them for cancer. When breast cancer spreads, it most often goes to the lymph nodes under the arm. A sentinel node biopsy removes some of those lymph nodes for testing. An axillary lymph node dissection removes most of the underarm lymph nodes.
You may choose to have breast reconstruction after mastectomy surgery. Breast reconstruction is surgery to restore shape to the breast. Options might include reconstruction with a breast implant or reconstruction using your own tissue. Consider asking your healthcare team for a referral to a plastic surgeon before your breast cancer surgery.
Estrogen blocker therapy
Estrogen blocker therapy treats breast cancers that use hormones to grow. It also is called endocrine therapy.
This treatment is often used for TPBC since it is hormone receptor positive. Estrogen blocker therapy may be used before surgery to shrink the cancer. It also may be used after surgery and other treatments to lower the risk that the cancer will come back.
If the TPBC spreads to other parts of the body, estrogen blocker therapy can help control it.
Estrogen blocker therapy treatments can include:
- Medicines that block or destroy hormone receptors. These medicines are called selective estrogen receptor modulators.
- Medicines that lower hormone production. These medicines are called aromatase inhibitors.
- Surgery or medicines to stop the ovaries from making hormones.
Radiation therapy
Radiation therapy treats cancer with powerful energy beams. The energy can come from X-rays, protons or other sources.
Radiation therapy for breast cancer often uses external beam radiation. During this type of radiation therapy, you lie on a table while a machine moves around you. The machine directs radiation to precise points on your body.
For TPBC, radiation therapy may be used after surgery. It can kill any cancer cells that might be left after surgery. The radiation lowers the risk of cancer coming back.
Chemotherapy
Chemotherapy treats cancer with strong medicines. Many chemotherapy medicines exist. Chemotherapy for breast cancer often involves a combination of medicines. Most are given through a vein. Some are available in pill form.
Chemotherapy may be used after surgery to treat TPBC. It can kill any cancer cells that might remain and lower the risk of the cancer coming back.
Sometimes chemotherapy is given before surgery. This may help shrink the cancer so that surgery is possible or so that you might consider a less extensive surgery. It also gives the care team a chance to see how the cancer responds to medicines. How the cancer responds to chemotherapy before surgery helps the healthcare team make decisions about what treatments might be needed after surgery.
When the cancer spreads to other parts of the body, chemotherapy can help control it. Chemotherapy may relieve symptoms of an advanced cancer, such as pain.
Targeted therapy
Targeted therapy medicines may help treat this cancer by attacking cells that make too much HER2 protein. Targeted therapy uses medicines that act on specific features of cancer cells that help them grow. By blocking these chemicals, targeted treatments can cause cancer cells to die.
Targeted therapy medicines may be used before surgery to shrink the cancer and make it easier to remove. Some are used after surgery to lower the risk that the cancer will come back. Others are used only when the cancer has spread to other parts of the body.
Cancer prognosis describes how likely it is that a cancer can be treated successfully or cured. Healthcare professionals estimate prognosis using information about the cancer and your overall health. To better understand your personal prognosis, talk with your healthcare team. The team can explain the factors that affect your situation.
Things that can affect the prognosis for breast cancers in general include:
- Cancer grade. Grade 1 and 2 cancers tend to grow more slowly and have a better prognosis than grade 3 cancers.
- HER2 status. HER2-positive cancers can grow quickly, but medicines that target HER2 may have improved outcomes.
- Hormone receptor status. Cancers that are hormone receptor positive typically have a better prognosis than those that are not.
- The size of the cancer in the breast. A small cancer may be easier to remove completely and have a lower risk of spreading.
- Whether the lymph nodes contain cancer. Cancer that spreads to the lymph nodes has a higher risk of spreading to other parts of the body. If the cancer hasn't spread to the lymph nodes, the prognosis is typically better.
What you can do
After treatment, your healthcare team may recommend healthy habits such as eating a balanced diet, staying active, maintaining a weight that is healthy for you and limiting alcohol.
Try to:
- Avoid or limit alcohol. For breast cancer prevention, there is no safe amount of alcohol. If you're concerned about your breast cancer risk, you may choose not to drink alcohol.
- Follow a healthy diet. Choose a diet that's rich in fruits, vegetables and whole grains. Limit how much red meat, processed meat and sugar you eat.
- Stay active. Aim to exercise most days of the week. If you don't exercise regularly, get your healthcare professional's OK first. Start out with short sessions of an activity you enjoy and build up the amount of exercise over time.
- Find your healthy weight. Ask your healthcare professional what weight range is healthy for you. If weight loss is recommended, ask about safe, achievable changes.
Talk with your healthcare team about other things you can do to lower your risk of recurrence. Also follow your care team's advice on follow-up exams and tests after you finish cancer treatment.
Alternative medicine
No alternative medicine treatments have been found to cure triple-positive breast cancer (TPBC) or other types of breast cancer. But complementary and alternative medicine therapies may help you cope with treatment side effects.
Alternative treatments for hot flashes
Hot flashes are bouts of sudden, intense warmness that can leave you feeling sweaty and uncomfortable. They can be a symptom of natural menopause or a side effect of estrogen blocker therapy, which is often used to treat triple-positive breast cancer.
Talk to your healthcare professional if you experience hot flashes. Many conventional treatments are available for hot flashes, including medicines.
If treatments for hot flashes don't work as well as you'd like, it might help to add complementary and alternative treatments to help you feel better.
Options might include:
- Acupuncture.
- Breathing exercises.
- Hypnosis.
- Meditation.
- Relaxation techniques.
- Tai chi.
- Yoga.
These alternative treatments have not been scientifically proved to help control hot flashes, but some people who have had breast cancer report that they help.
If you're interested in trying alternative treatments for hot flashes, talk to your healthcare team about your options.
Coping and support
Learning that you have triple-positive breast cancer (TPBC) can bring many emotions and questions about what comes next. It's common to have a range of feelings that may change from day to day. And it can take time to process everything. As you move forward, here are some ideas that might be helpful.
Learn what you need to make decisions about your care
If you'd like to know more about your cancer, ask your healthcare team for the details. Write down the type and stage. Ask for good sources of information where you can learn more about your treatment options.
Knowing more about your TPBC and your options may help you feel more confident when making treatment decisions. Still, some people don't want to know the details of their cancer. If this is how you feel, let your care team know that too.
Find a good listener
Talking with someone you trust may help as you manage a TPBC diagnosis. This could be a friend, family member, counselor, medical social worker or faith leader.
Talk with other breast cancer survivors
You may find it helpful and encouraging to talk to others who have been diagnosed with TPBC or other types of breast cancer. Ask your healthcare team about support groups in your area. Or contact the American Cancer Society or another cancer organization in your area to find resources. Find support online through Mayo Clinic Connect, a community where you can connect with others for support, practical information and answers to everyday questions.
Preparing for an appointment
Make an appointment with a doctor or other healthcare professional if you have any symptoms that worry you. If an exam or imaging test shows you might have TPBC, your healthcare team will likely refer you to a specialist.
Specialists who care for people with breast cancer include:
- Breast health specialists.
- Breast surgeons.
- Doctors who specialize in diagnostic tests, such as mammograms, called radiologists.
- Doctors who specialize in treating cancer, called oncologists.
- Doctors who treat cancer with radiation, called radiation oncologists.
- Genetic counselors.
- Plastic surgeons.
What you can do to prepare
- Write down any symptoms you're experiencing, including any that may seem unrelated to the reason for which you scheduled the appointment.
- Write down key personal information, including any major stresses or recent life changes.
- Make a list of all medicines, vitamins or supplements that you're taking and the doses.
- Keep all of your records that relate to your cancer diagnosis and treatment. Organize your records in a binder or folder that you can take to your appointments.
- Consider taking a family member or friend along. The details of managing breast cancer can be overwhelming. Sometimes it can be difficult to remember all the information given during an appointment. Someone who goes with you may remember something that you missed or forgot.
- Write down questions to ask your healthcare professional.
Questions to ask your healthcare professional
Your time with your healthcare professional is limited. Prepare a list of questions so that you can make the most of your time together. List your questions from most important to least important in case time runs out. For triple-positive breast cancer some basic questions to ask include:
- What should I know about triple-positive breast cancer?
- What is the stage of my cancer?
- Can you explain my pathology report to me? Can I have a copy for my records?
- Do I need any more tests?
- What treatment options are available for me?
- What are the benefits and risks of each treatment you recommend?
- What are the side effects of each treatment option?
Other questions could include:
- How will each treatment option affect my daily life? Can I continue working?
- Is there one treatment you recommend over the others?
- How do you know that these treatments will benefit me?
- What would you recommend to a friend or family member in my situation?
- How quickly do I need to make a decision about cancer treatment?
- What happens if I don't want cancer treatment?
More questions to ask may include:
- What will cancer treatment cost?
- Does my insurance plan cover the tests and treatment you're recommending?
- Is there someone from your business office I can talk to about the treatment cost details?
- Should I seek a second opinion? Will my insurance cover it?
- What websites or books about my cancer do you recommend?
- Are there any clinical trials or newer treatments that I should consider?
In addition to the questions that you've prepared, don't hesitate to ask other questions you think of during your appointment.
What to expect from your healthcare professional
Be prepared to answer some questions about your symptoms and your health, such as:
- When did you first begin experiencing symptoms?
- Have your symptoms been continuous or occasional?
- How severe are your symptoms?
- What, if anything, seems to improve your symptoms?
- What, if anything, appears to worsen your symptoms?
Stages
Once your healthcare team diagnoses triple-positive breast cancer (TPBC), you may have tests to learn how far the cancer has spread. This process is called staging.
Complete information about your cancer's stage may not be available until after breast cancer surgery.
Tests and procedures used to stage TPBC may include:
- Blood tests, such as a complete blood count and tests to show how well the kidneys and liver are working.
- Bone scan.
- CT scan.
- MRI.
- Positron emission tomography (PET) scans, including fluoroestradiol (FES) PET scan to detect advanced breast cancer that is estrogen receptor positive.
Not everyone needs all of these tests. Your healthcare team picks the tests based on your specific situation.
Information used in staging includes:
- The size of the cancer in the breast.
- Whether cancer cells have spread to the lymph nodes or other parts of the body.
- The cancer's grade.
- The cancer's hormone receptor status.
- The cancer's HER2 status.
- The presence of certain genes that might affect treatment options.
- Other pieces of information that may become available after the cancer is removed during surgery.
Types of staging
The process of breast cancer staging can take place at different times after diagnosis and around treatment. Your stage may change as your care team gets more information about your cancer.
Healthcare professionals use different types of stages at different times. This may include:
- Anatomic staging happens after a breast biopsy confirms cancer. It tells your care team about the size of the cancer and whether it has spread. It does not take cancer grade, hormone receptor status or HER2 status into account.
- Clinical prognostic staging uses the test results available before treatment, including grade, hormone receptor status and HER2 status, to help plan care.
- Pathological prognostic staging is used after surgery once the cancer is removed. This kind of staging looks at factors such as the size of the cancer removed during surgery and the number of lymph nodes removed that contain cancer.
- Postneoadjuvant therapy prognostic staging or staging after treatment given before surgery describes the cancer after that treatment and helps plan next steps.
Because there are several types of stages that consider different factors, the stages of breast cancer can be confusing and complicated. Ask your healthcare team to explain your stage and what it means for your treatment.
Anatomic stages
Anatomic staging is the simplest form of breast cancer staging. To decide on the anatomic stage, the healthcare team uses the size of the cancer and whether it has spread. Using this type of staging, the stages go from 0 to 4.
- Stage 0. Cancer cells have not spread.
- Stage 1. The cancer in the breast is less than 1 inch (2 centimeters) in diameter. Cancer cells have spread beyond ducts into the breast tissue. There is little or no evidence of cancer in the lymph nodes. Cancer has not spread elsewhere in the body.
- Stage 2. The cancer in the breast is less than 2 inches (5 centimeters) in diameter and has spread to some underarm lymph nodes.
- Stage 3. The cancer in the breast is any size and has spread to many underarm lymph nodes. Or the cancer is larger than 2 inches (5 centimeters) in diameter and has spread to some underarm lymph nodes. This stage also includes cancers that spread to the skin, the chest beyond the muscle or the lymph nodes inside the chest wall. Inflammatory breast cancer is considered a stage 3 cancer.
- Stage 4. The cancer in the breast is any size, and cancer cells have spread to sites away from the breast and nearby lymph nodes. These sites may include the brain, bones, lungs or liver.
The anatomic stage may be the first stage your healthcare team talks about after your diagnosis. The stage may change as your team gets more information about your cancer, such as the hormone receptor status.
Grades
A cancer's grade is a number that tells the healthcare team how different the cancer cells look from healthy cells. The grades of breast cancer, including triple-positive breast cancer, go from 1 to 3.
To decide on the grade, doctors in the lab, called pathologists, use a microscope to look at the cancer cells from a biopsy. If the cancer cells look similar to healthy cells, then the cancer cells are low grade. Low-grade cancer grows slowly. If the cancer cells look very different from healthy cells, then the cancer cells are high grade. High-grade cancer grows quickly.
The grades include:
- Grade 1. Grade 1 is a low grade. The cancer cells look similar to healthy cells. Grade 1 typically grows slowly and has a low risk of spreading. It's sometimes called well-differentiated cancer.
- Grade 2. Grade 2 is an intermediate grade. The cancer cells look a little different from healthy cells. Grade 2 grows more quickly than grade 1 cancer. It also has a higher risk of spreading. Sometimes it's called moderately differentiated cancer.
- Grade 3. Grade 3 is a high grade. The cancer cells look very different from healthy cells. Grade 3 is considered a fast-growing cancer. It has the highest risk of spreading. Sometimes it's called poorly differentiated cancer.
The grade of triple-positive breast cancer helps the healthcare team understand the prognosis and make a treatment plan.
Survival rates
The survival rates for triple-positive breast cancer (TPBC) and other types of breast cancer are more favorable when the cancer is found early.
Sometimes people diagnosed with cancer want to know about survival rates. Some people find survival statistics helpful. Others find them confusing, discouraging or overwhelming. It is OK to choose how much information you want.
Survival statistics can provide general information about the seriousness of the situation, but they can't predict what will happen to any one person. These statistics include thousands of people with breast cancer, including people of different ages, with different health conditions and with different treatment histories.
Keep in mind that your healthcare team uses much more detailed information when talking with you about your individual prognosis and treatment options.
The healthcare team cannot provide specific survival numbers for any one patient. But the team can provide a range of survival in groups of patients. That may be helpful for your future planning.
Survival statistics
The U.S. National Cancer Institute (NCI) tracks cancer survival rates in the United States. These survival rates come from NCI data for the broader HR-positive/HER2-positive group that TPBC is part of. NCI reports based on how far the cancer has spread.
- Localized cancer, which means the cancer is only in the breast, has a five-year relative survival rate of 99.5%.
- Regional cancer, which means the cancer has spread to nearby lymph nodes, has a five-year relative survival rate of 91.5%.
- Distant cancer, which means the cancer has spread to other parts of the body, has a five-year relative survival rate of 48.7%.
These rates describe large groups of people with breast cancer. They cannot predict what will happen to you. Your outlook depends on the details of your TPBC, your health and how well the treatment destroys the cancer.
© 1998-2026 Mayo Foundation for Medical Education and Research(MFMER). All rights reserved. Terms of Use