
X-linked agammaglobulinemia
Conditions
Overview
X-linked agammaglobulinemia (a-gam-uh-glob-u-lih-NEE-me-uh) is a rare condition that makes it hard to fight infections. The immune systems of people with this condition make very few disease-fighting proteins called antibodies.
X-linked agammaglobulinemia (XLA) is usually an inherited condition. This means it's passed down through families. XLA most often affects males.
XLA is usually diagnosed during infant or toddler years after a child has had repeat illnesses caused by germs. The main treatment uses antibodies from healthy donors to help the body fight infections.
XLA is one of several conditions called primary immunodeficiencies.
Symptoms
Most babies with XLA appear healthy for the first few months. A child is protected by antibodies from the mother before birth and for a few months after birth. When those antibodies break down, the child's body isn't able to make its own.
From 3 to 18 months, illnesses caused by germs may happen more often. These infectious diseases may be severe, long-lasting or difficult to treat. Illnesses of children with XLA can include:
- Ear infections.
- Sinus infections.
- Strep throat.
- Pneumonia.
- Infections or parasites in the digestive system.
- Infections in the bloodstream.
- Infections of the skin or other organs.
People with XLA also may have very small disease-fighting tissues, including:
- Tonsils.
- Adenoids.
- Glands in the neck called lymph nodes.
These tissues are small because they lack the cells that make antibodies.
Causes
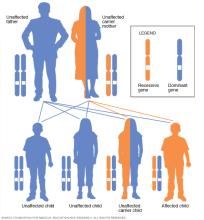
XLA is caused by a change in a gene called a mutation. Genes are like sentences in the body's instruction manual. A mutation is like a misspelled word in a sentence that changes how cells are put together or how they work.
The XLA-related gene mutation causes the body to make very few mature white blood cells called B cells. Mature B cells make proteins called antibodies. Antibodies target bacteria, viruses, fungi and parasites that can cause diseases. With few or no B cells, there are almost no antibodies. Without antibodies, the body cannot fight infections.
The gene mutation that causes XLA is on the X chromosome. Typically, a male gets one X chromosome from the mother and one Y chromosome from the father. A female typically gets two X chromosomes, one from each parent.
The most common pattern of inheritance of XLA is that a boy gets an XLA gene mutation on the X chromosome from his mother. Having this one mutation causes the condition.
A girl may inherit an X chromosome with the XLA gene mutation from her mother, but the X chromosome from the father would ensure that she can still make mature B cells. Although she would not have XLA, she would carry the gene mutation and could pass it on.
A girl could get XLA if she got the gene mutation from both parents. This would be very rare.
A related condition called autosomal agammaglobulinemia also happens because the body can't make mature B cells. The gene mutation that causes this is on a chromosome other than the X or Y chromosomes. Males and females can have this rare condition.
In some cases, a random change in a gene may cause XLA. In this case, it is not passed down by a parent.
Risk factors
The primary risk of XLA is that a mother is a carrier of an XLA-related gene mutation. A risk of XLA may be known in a family, particularly if the mother has brothers or maternal uncles or cousins with the condition.
Families may want to have genetic counseling. This means working with a specialist who can help them understand the benefits and risks of genetic testing. The specialist also helps interpret results.
Complications
With ongoing treatment, people with XLA can live mostly typical lives. They usually can take part in regular activities for their ages.
Even with therapy, repeat infections occur. This requires regular monitoring and prompt treatment.
XLA and repeat infections may lead to long-term complications, including:
- Ongoing lung disease.
- Ongoing inflammation of the sinuses.
- Arthritis.
- Thyroid disease.
- Inflammatory bowel disease.
- Certain cancers.
Diagnosis
A diagnosis of repeat and prolonged infections begins with a history of infections, a complete physical and a review of family medical history. This will include an exam of the tonsils, adenoids and lymph nodes in the neck.
If your healthcare professional suspects X-linked agammaglobulinemia (XLA) or another immune system condition, blood samples are sent to a lab to measure levels of:
- Mature B cells.
- Overall antibodies.
- Specific antibodies to common illnesses.
- Antibodies that would be expected based on vaccine history.
If blood tests show a likely diagnosis of XLA, a genetic test is done to find the specific XLA gene mutation.
Treatment
There's no cure for XLA. Treatment goals are:
- Boosting the immune system to prevent infections.
- Treating infections promptly.
- Watching for possible long-term complications at regularly scheduled follow-up visits.
Immunoglobulin (Ig) replacement therapy
Ig replacement therapy is the main treatment for XLA. This therapy gives you antibodies, also called immunoglobulins, from a pool of thousands of donors. This replaces many but not all typical antibodies. It can help fight many different infections.
Ig replacement therapy is given as a shot into the fatty tissues under the skin or through an IV line in a vein. The therapy is done every 2 to 4 weeks to resupply the immune system with antibodies.
The treatment has some limitations. It doesn't replace all types of antibodies made by the immune system. It doesn't protect against uncommon diseases or new germs. It doesn't correct the immune system process of making antibodies, and there isn't the typical boost in antibodies when someone gets an infection.
Possible side effects of injections include burning or swelling at the injection site. Side effects of an IV route may include chills, stiffness, blood pressure changes, nausea, vomiting and general achiness.
Antibiotics
Antibiotics are prescribed to treat infections when they happen. The treatments may have higher doses or longer courses of treatment than is typical. Some people with XLA take antibiotics regularly to prevent infection.
Vaccines
A regular course of vaccines is recommended, as well as annual flu and COVID-19 vaccines. While the immune system will likely not create the typical antibodies to infections, they may trigger other immune system responses that help fight diseases.
People with XLA cannot get vaccines with live viruses. There is some risk for a person with XLA of developing the disease, particularly polio, from this type of vaccine.
Close family members are encouraged to get all regularly scheduled and annual vaccines to help prevent the spread of germs to the person with XLA.
Lifestyle and home remedies
Lifestyle practices can help prevent disease. These are lifelong habits that you can teach and model for your child.
- Wash hands with soap and water:
- Before and after meals.
- Before preparing food.
- After blowing your nose or coughing.
- After using the toilet or changing a diaper.
- After handling garbage.
- Use hand sanitizer when soap and water aren't available.
- Brush teeth twice a day, and see the dentist at least twice a year.
- Avoid crowds, particularly during the cold, flu and COVID-19 season.
- Avoid social events among people who do not get vaccinations.
- Wear masks, particularly during the cold, flu and COVID-19 season.
- Wash produce and handle raw meat carefully.
Coping and support
While most people with XLA can lead typical lives, the condition requires lifelong, consistent illness prevention and care. It may result in absences from school, work or recreational activities. This can cause stress for a child and later, the teen or adult.
Talk with your child about what XLA means in age-appropriate terms. Listen to any worries or concerns your child may have. Help your child learn language to talk about the condition.
The Immune Deficiency Foundation provides resources for families to learn about XLA and other immune system conditions, find community support, and learn coping skills.
Preparing for an appointment
You'll likely start with your child's primary healthcare professional. You also may see specialists in genetics, infectious diseases and immune system conditions.
Here's some information to help you get ready for your appointment.
What you can do
Make a list of your child's:
- Current symptoms.
- History of past illnesses.
- Medicines currently prescribed and prescribed in the past.
- Vaccine history.
- Family history of frequent illnesses or immune system conditions.
Take a family member or friend along, if possible, to take notes and help you remember the information you're given.
What to expect from your doctor
Your healthcare professional is likely to ask you several questions, such as:
- When was your child's last wellness visit?
- What illnesses has your child had?
- How often did your child have each illness?
- How were the illnesses treated?
- What antibiotics were prescribed? How long was the treatment plan?
- What vaccines has your child had?
- Is there a history of an immune system condition in the family? Who was affected?
- Is there a history of frequent infectious disease among the family? Who was affected?
© 1998-2026 Mayo Foundation for Medical Education and Research(MFMER). All rights reserved. Terms of Use